When Aisha Durham, a professor of communication at the University of South Florida, entered perimenopause in her 40s, she began noticing changes in her body—a not uncommon occurrence for many women at this stage of life as hormone levels shift. But Durham sensed these changes were something else, given the severity of her symptoms.
First came the inflammation: swelling she describes as pervasive and so painful, at times, that she spent days bedridden. Next came the nodules: small, hard bumps that trailed up and down her legs.
Visits to multiple doctors resulted in a litany of diagnoses—and misdiagnoses. One physician suspected the chronic inflammation was due to undifferentiated connective tissue disease (UCTD), a systemic autoimmune disorder, and put her on hydroxychloroquine as treatment. (It wasn’t UCTD.) Another looked at Durham and told her she was simply fat, and that her fat stores were shifting due to perimenopause. (It wasn’t “typical” fat.) A third surmised Durham’s pain was due to fibromyalgia. (It wasn’t fibromyalgia.) The nodules in Durham’s legs were, at turns, diagnosed as a spider bite and an allergic reaction. (Wrong on both counts.)
A dutiful patient, Durham heeded doctor’s orders to overhaul her nutrition and exercise to lose weight. “I hired a dietitian. I did one-on-one pilates sessions, but everything was hurting,” she says. These lifestyle changes did little to relieve her symptoms, and after months of being misdiagnosed or dismissed entirely, Durham was desperate for any clues.
She had a hunch her chronic inflammation might have something to do with fluctuating hormone levels, and after falling down a YouTube rabbit hole, she landed on a scholarly presentation by endocrinologist Karen Herbst, MD. In that video, Durham found her answer.
“She showed pictures, and I said, ‘Those legs look like mine,’ ” Durham recalls.

The photos? They depicted patients who had been diagnosed with lipedema, a chronic, incurable condition that affects mostly women and is characterized by a disproportionate and symmetrical buildup of often painful fat in the lower body and sometimes in the arms and/or lower trunk.
The imagery was a revelation for Durham, who decided then and there that if none of her local doctors would take her seriously, she would fly to Arizona for a consultation with Dr. Herbst herself. About six months later, in Dr. Herbst’s office, she got the diagnosis she’d been relentlessly seeking: stage 2 lipedema.
“I cried,” Durham says of the moment. “I felt lighter. It didn’t get rid of the condition at all. It didn’t make it better. But it was just so relieving to have a doctor confirm what I was experiencing.”
Cases like Durham’s are not unusual. Though it’s estimated that around 5 to 12 percent of women in the U.S. have lipedema, it still takes, on average, about 10 years to receive a diagnosis, according to the Lipedema Foundation, which is dedicated to advancing research and awareness of lipedema. That delay is due to a lack of awareness around the condition as well as frequent misdiagnoses. That’s a decade of doctor visits, patronizing dismissals, and unnecessary pain. And even then, a diagnosis is just the first step in what will likely be a long journey of managing or mitigating symptoms—one that is often emotionally, mentally, physically, and financially fraught.

An Underrecognized Disorder
Despite so many American women walking around with lipedema, few have heard of it or been given any reason to suspect the dimpling on their legs is anything other than cellulite. Though the condition has drawn a few headlines recently—singer Doja Cat speculated on TikTok earlier this year that she may have lipedema—it still remains a largely under-the-radar and underdiagnosed condition.
It might be surprising to learn, then, that lipedema isn’t a new disorder. It was first described by two Mayo Clinic physicians, Dr. Edgar V. Allen and Dr. Edgar A. Hines, in 1940. And researchers say artworks from as far back as 3,000 BC have recorded the telltale pear shape of the lipedema body—slim torsos punctuated by almost cartoonishly large hips, thighs, and butts—suggesting that even bygone civilizations recognized lipedema, even if they may not have had a name for it.
The tag that Dr. Allen and Dr. Hines landed on is a portmanteau of lipid (fat) and edema (swelling). It’s a bit of an unfortunate moniker given its closeness to a separate yet similar condition called lymphedema, which causes abnormal, usually asymmetrical tissue swelling. But they are, in fact, two distinct diseases, so in order to distinguish them, some in the lipedema community have tried brainstorming a new name (none have stuck), while others have leaned into a pronunciation in which the first syllable rhymes with “sky” rather than “skip.” (The American English pronunciation is generally LIP-uh-DEEM-uh, though if you talk to enough people about it, you’ll likely hear it pronounced both ways.) To confuse matters even further? In some cases, lipedema and lymphedema may present as comorbidities in a patient. (More on that in just a bit.)
There’s no known cause for lipedema, though it’s generally considered to have a strong genetic component. It often shows up—or worsens—during periods of hormonal fluctuation. An easy mnemonic device to remember for this is the three P’s: puberty, pregnancy, and peri/menopause. It’s widely believed to be a connective tissue disorder, but that still seems up for debate. It’s also been tentatively (and, in many cases, anecdotally) linked to a host of comorbidities, including hypermobility, Ehlers-Danlos syndrome, ADHD, and polyendocrine metabolic ovarian syndrome (PMOS, formerly called PCOS). Again, more research is needed.
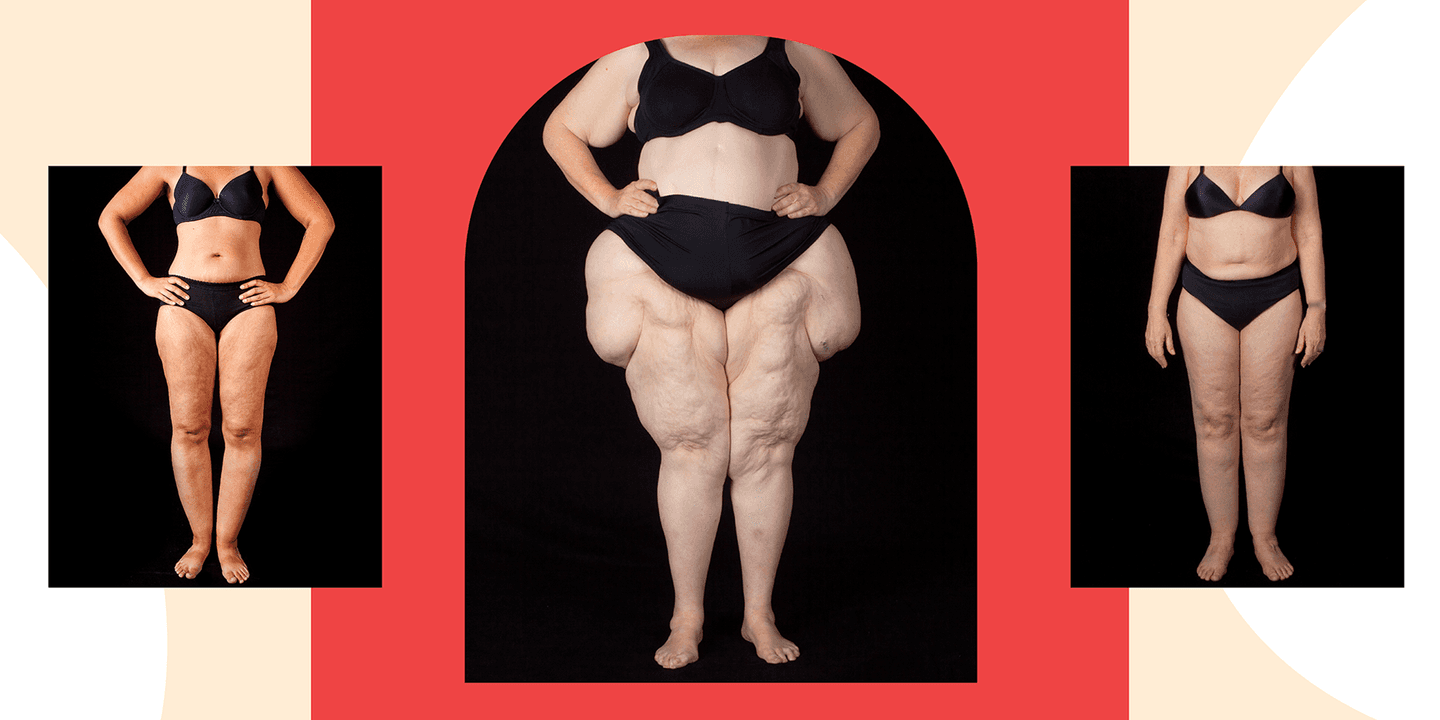
Lipedema is diagnosed by type and in stages. Type indicates where the fat is located on the body. Type I is fat between the belly button and hip. Type II is fat between the pelvis and knee. Type III is fat between the pelvis and ankle. Type IV is fat between the shoulder and wrist. Type V is fat between the knees and ankles. Stage indicates the severity of symptoms. Stage 1 is some accumulation of soft subcutaneous fat with largely smooth skin that might have small nodules under the surface. Stage 2 is more severe dimpling or indentations with larger, more prominent nodules and hardened fat deposits that may be fibrotic. Stage 3 is marked by larger fat deposits that may start to overhang or otherwise noticeably extrude from the body. And then there’s stage 4, which is also known as lipolymphedema, which, as hinted above, occurs when both lipedema and lymphedema are present.
Women may progress all the way to stage 4 or stay fixed in an earlier stage. Some may feel no pain with lipedema; others may feel intense pain during flare-ups. How and why lipedema progresses in some and not others is still one of the mysteries researchers are unraveling. In some cases, the pain and deformities caused by this excess fat accumulation can become so extreme that a woman struggles to walk or go about the daily tasks of life.
“I have several family members who are fully disabled by this disease to the point of being in wheelchairs or having to walk with walkers or walking aids,” says Kasi Grosvenor, a 45-year-old project manager in Richmond, Virginia, who was diagnosed with lipedema at the age of 40. “I’ve watched the progression of this disease through many family members up my dad’s line—that is the line where it came in our family—and I didn’t want to get there too.”

Lipedema is diagnosed in stages, based on progression of the condition. Examples of the stages (clockwise, from top left): stage 1, stage 2, stage 3, and stage 4.
A Much-Delayed Diagnosis
So why does it typically take so long for women (the condition is rare in men, FYI) to receive a lipedema diagnosis? Infuriating stat alert: The average age for diagnosis, per the Lipedema Foundation’s registry, is 48. As in the case with many underdiagnosed and misunderstood women’s health conditions—be it PMOS or endometriosis—much of the delay can be traced back to systemic issues that don’t have a quick or simple solution, says Jonathan Kartt, CEO of the Lipedema Foundation.
“Lipedema really sits at the intersection of two areas that medicine has always been really slow to fund and slow to take seriously, and those are chronic disease and conditions that primarily impact women,” he says.
Indeed, a surprising number of clinicians are as unaware of lipedema as the average Jane on the street. “Medical schools really didn’t historically teach it,” Kartt says. While certain specialties, like vascular medicine, do have relevant training, Kartt says the real gap is primary care—often a patient’s first stop on the road to a diagnosis.
Another barrier to diagnosis is the lack of diagnostic tests for lipedema. Peeing in a cup, swabbing your mouth, or rolling up your sleeve for a blood draw will get you nowhere. Diagnoses are made through a thorough review of the patient’s medical history as well as an exam. Physicians will typically do a visual assessment (checking for signs like irregular fat distribution) and a physical assessment (feeling for nodules or fibrosis, which distinguish lipedema fat from run-of-the-mill cellulite).
If a physician does suspect a patient has lipedema, there’s yet another hurdle: In the U.S., there’s no diagnostic code for lipedema. The World Health Organization has classified lipedema as a distinct disease in the International Classification of Diseases (ICD-11), but the U.S. is still using the older ICD-10, which does not. While that might sound like a simple paperwork issue, it’s much more consequential than that. Diagnostic codes are necessary for insurers to determine that they will pay for particular procedures or treatments relevant to the diagnosis. Without a code, the patient may be left to pay for their treatments out of pocket or go without treatment altogether. To get around this, clinicians have had to get creative in their diagnostics, using codes for similar or blanket conditions (such as edema).
“If we want to give a woman a diagnosis of lipedema, we really have to give her six or seven different codes that look like lipedema codes,” says Sarah Whitehead, an advanced registered nurse practitioner and founder of Lumina Vascular Health & Laser Clinic.
Diagnostic codes also help researchers track the prevalence of a disease, which is one reason why estimates of lipedema sufferers always have an asterisk next to them (depending on which study you read, rates vary from the single digits up to 39 percent). But there is some hope: The Centers for Disease Control and Prevention have approved a dedicated code for lipedema that should go into effect in October 2027.
“That sounds small, but it changes everything downstream,” Whitehead says. “It lets us count how many women are affected and make a real case for research funding.” She cautions, however, that true change will require updated insurance policies around the code so women can actually access care.
One final (and big) reason many women struggle to get a lipedema diagnosis: A physician untrained in lipedema may conflate the condition with obesity. While the two can coexist and frequently do, lipedema fat behaves much differently than regular fat. It generally doesn’t respond to diet and exercise, meaning there’s no real way to “burn” it off. So dismissing lipedema as simply an issue of needing to lose a few pounds is not only plain wrong (especially given that women at any BMI can have lipedema), but it’s also caused many to needlessly suffer from painful symptoms for decades.
