The East African country’s HIV progress is running into a stubborn diagnosis gap, as prevalence stands at 7.3% among women and 4.1% among men
COVER STORY | RONALD MUSOKE | Uganda’s HIV prevalence among adults aged 15 years and above has remained at 5.9%, with women almost twice as likely as men to be living with the virus, according to preliminary findings from the country’s latest national HIV survey.
The findings of the 2025 Uganda Population-Based HIV Impact Assessment (UPHIA 2025), released by the Ministry of Health on Oct. 1, show that an estimated 1.496 million Ugandan adults are living with HIV. Prevalence stands at 7.3% among women and 4.1% among men.
The results present a mixed picture of the country’s HIV response. While Uganda has made substantial progress in getting people diagnosed with HIV onto treatment and achieving viral suppression, the proportion of people living with HIV who know their status remains below the national target.
The survey found that 85.3% of adults living with HIV knew their status, against a target of 95%. However, 99.1% of those who knew their status were receiving antiretroviral treatment, while 96.5% of those on treatment had achieved viral suppression.
For the government, the results point to a shift in priorities; sustaining treatment gains while finding people who remain undiagnosed, improving prevention and addressing persistent disparities among young people and across the country’s regions. Presenting the preliminary findings at the Uganda Media Centre in Kampala, Dr Chris Baryomunsi, the Minister of Health, described the survey as an accountability tool for the next phase of Uganda’s health reforms.
“The headline message is encouraging, but it is also clear about where we must focus,” he said. “Almost everyone who knows they are living with HIV is on treatment, and almost everyone on treatment has suppressed the virus. Our biggest remaining gap is at the very start: about one in seven people living with HIV do not know their status.”
The survey was conducted between July and September 2025, and its findings come at a critical point in Uganda’s ambition to end AIDS as a public health threat by 2030. However, the preliminary results do not yet establish whether the number of new infections is declining, since the detailed HIV incidence findings are still awaited.
Prevalence has stopped declining
The latest figures suggest that the substantial decline in HIV prevalence recorded over previous decades has given way to a period of relative stability. Among adults aged 15 to 49, HIV prevalence was 5.5%, unchanged from the 2020/2021 UPHIA survey. The corresponding figures in the 2016/2017 assessment were 6.0% overall, 7.5% among women and 4.3% among men. In 2020/2021, prevalence among this age group was 5.5%, with women at 7.1% and men at 3.8%. The longer-term decline has been substantial. But the latest survey suggests that prevalence is no longer falling at the same pace, even as treatment outcomes improve.
In the 2025 assessment, prevalence among all adults aged 15 and above was 5.9%, equivalent to approximately 1.496 million people living with HIV. The distinction between prevalence and incidence is important. Whereas prevalence measures the proportion of a population living with HIV at a particular time, including people who acquired the virus years earlier and are still alive, incidence measures new infections over a specified period. In other words, a stable prevalence rate does not, on its own, establish that new infections have stopped declining. Improved treatment and longer survival can also affect the number of people living with HIV.
The final UPHIA report is expected to provide further information on incidence, programme coverage and behavioural indicators, which will help establish whether prevention efforts are reducing new infections and where additional interventions are required. The latest findings therefore offer a snapshot of the epidemic’s current scale and the performance of the treatment programme, rather than a complete explanation of why prevalence has stabilised.
Uganda misses the first 95 target
The clearest weakness identified by the survey is the gap between people living with HIV and those who know their status. The 95-95-95 targets, established as part of international efforts to control the epidemic, aim for 95% of people living with HIV to know their status, 95% of those diagnosed to receive antiretroviral treatment, and 95% of those receiving treatment to achieve viral suppression.
UPHIA 2025 found that Uganda had reached 85.3% on the first measure, 99.1% on the second and 96.5% on the third. The country has therefore exceeded the treatment and viral suppression targets among adults aged 15 and above, but has not reached the diagnosis target. The difference matters because people who do not know their HIV status may miss opportunities to access treatment and prevention services. Identifying them and linking them to care is essential to closing the remaining gap.
Dr Diana Atwine, the Permanent Secretary of the Ministry of Health said the findings would help the government identify where to concentrate its efforts in the next phase of the response. “We do believe that these results are a true reflection of what is happening in our country as far as the HIV status is concerned,” she said. “And we do believe that it will give us a very clear direction and the roadmap that we are going to take in the next five years to target and to get our targets achieved.”

Dr Atwine said the survey would help the ministry identify people who had not been diagnosed and strengthen efforts to reach them. The challenge is not simply to increase the number of people tested. Testing must be accompanied by appropriate counselling, timely linkage to treatment for those diagnosed, and sustained access to care.
The survey’s results also suggest that the quality of the response should be assessed beyond the number of people enrolled on treatment. The age and regional differences in viral suppression show that national progress can conceal gaps among particular populations.
Treatment outcomes improve, but young people lag
The survey found that 86% of all adults aged 15 and above living with HIV had achieved viral suppression, regardless of whether they knew their status or were receiving antiretroviral treatment. That compares with 75.4% in the 2020 survey. Viral suppression means that treatment has reduced the amount of HIV in a person’s blood to a low level. Maintaining suppression improves health and prevents sexual transmission of HIV when the virus remains undetectable.
The distinction between population-level viral suppression and suppression among people already on treatment is important. The former includes everyone living with HIV, including those who have not been diagnosed or linked to treatment. The latter measures outcomes among people receiving care.
Uganda’s 96.5% result among people on treatment indicates strong treatment outcomes within that group. The lower 86% population-level figure reflects the remaining gaps across the wider population of people living with HIV.
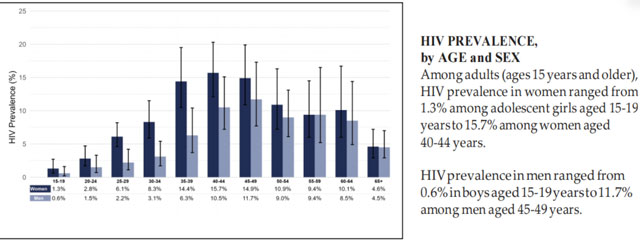
The survey found particularly low viral suppression among younger people living with HIV. Among women aged 15 to 24, viral suppression was 64.1%. The survey could not produce a reliable estimate for men living with HIV in the same age group because the numbers were too small. The findings also show substantial differences in HIV prevalence between younger age groups.
Among people aged 15 to 24, prevalence was 1.5%, with 2.0% among women and 1.0% among men. Among women aged 15 to 19, prevalence was 1.3%, rising to 2.8% among those aged 20 to 24. Among men, prevalence rose from 0.6% at ages 15 to 19 to 1.5% at ages 20 to 24.
These figures indicate that HIV prevalence is considerably higher among people in their early twenties than among younger adolescents. They do not, however, establish when individuals acquired the virus. The minister said the results called for prevention and testing interventions to reach young people earlier, particularly adolescent girls and young women.
The lower viral suppression recorded among young women living with HIV also raises questions about whether existing services are meeting the needs of younger patients. The preliminary findings identify the disparity but do not establish its causes. Possible explanations would need to be investigated rather than assumed. The final report and further research may help clarify the barriers affecting diagnosis, treatment access and adherence among younger people.
The wider findings show that the highest HIV prevalence was not among the youngest adults. Among men, prevalence peaked at 11.7% in the 45-to-49 age group; among women, it reached 15.7% among those aged 40 to 44. This means that the response must address both the higher prevalence among middle-aged adults and the specific prevention and treatment challenges facing younger populations.
Regional disparities remain pronounced
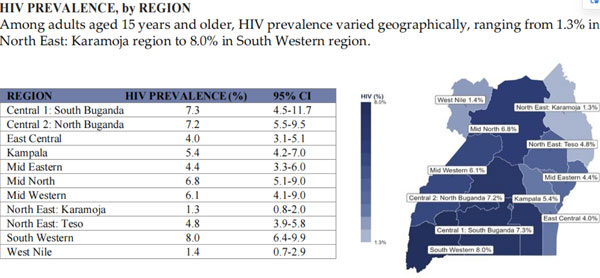
The national prevalence figure also conceals considerable variation between regions. The South-western region recorded the highest HIV prevalence, at 8.0%. The survey covering Wakiso, Mpigi and greater Masaka, recorded 7.3%, while the survey covering greater Mubende, Luweero and Mukono, recorded 7.2%.
Prevalence was 6.8% in Mid-North, 6.1% in Mid-Western and 5.4% in Kampala. The lowest figures were recorded in Karamoja in Northeastern Uganda, at 1.3%, and West Nile in Northwestern Uganda, at 1.4%. Viral suppression also varied geographically, ranging from 78.0% in Mid-Eastern Uganda to 92.3% in the South-Western region.
These differences matter for the allocation of resources. A national strategy that focuses only on the overall prevalence rate may overlook areas with higher burdens or populations facing greater difficulty accessing effective services.
The findings provide district and regional health planners with evidence to identify gaps in testing, treatment and prevention. However, the preliminary results do not explain the underlying reasons for each region’s prevalence or viral suppression levels. Those questions require further investigation.
Dr. Baryomunsi said the government would use the survey to direct available resources towards people and communities with the greatest needs and strengthen primary healthcare services. The survey’s value will therefore depend partly on how effectively its findings are translated into targeted interventions and measurable improvements in service delivery.
A survey designed to measure progress
UPHIA 2025 was the third round of Uganda’s population-based HIV impact assessments, following surveys conducted in 2016/2017 and 2020/2021. Unlike routine health-service data, which largely reflects people who use health facilities and are recorded by the health system, a population-based household survey can also reach people who are not regularly accessing services. This is particularly important for identifying people living with HIV who have not been diagnosed, assessing viral suppression across the population and examining differences by age, sex and geographical location.
The assessment was led by the Ministry of Health in collaboration with Makerere University School of Public Health, the Uganda Bureau of Statistics (UBOS), the Uganda Virus Research Institute (UVRI), regional referral hospitals, districts and other implementing partners. It was funded by the United States President’s Emergency Plan for AIDS Relief (PEPFAR) through the US Centers for Disease Control and Prevention. The survey used a sample of households intended to represent the Ugandan population. It was conducted across the country between July and September 2025.
According to the Ministry of Health’s preliminary results, 6,283 eligible households were identified, of which 94.4% participated. Among eligible adults aged 15 and above, 8,317 were women and 6,361 were men. Of those eligible, 96.2% of women and 91.2% of men were interviewed.
Among those interviewed, 97.8% of women and 97.4% of men were tested for HIV. Trained teams conducted household interviews and HIV testing using serological rapid tests in line with Uganda’s national HIV testing guidelines. Participants who tested positive were referred to antiretroviral treatment services.
The survey gathered information on HIV prevalence, viral suppression and uptake of prevention, testing, care and treatment services. It was designed to assess progress towards the 95-95-95 targets and identify gaps that should shape the next phase of the national response. The results are estimates drawn from a sample, rather than a test of every Ugandan. Their value lies in the survey’s population-based design, the participation achieved and the use of consistent methods to assess changes over time.
At the launch of the survey in May 2025, Prof. Rhoda Wanyenze, the Dean of Makerere University School of Public Health, highlighted the importance of building national research capacity. “This milestone builds on our experience from previous national surveys, including those on TB and family planning,” she said.
Prof. Wanyenze said the work reflected Uganda’s ability to conduct large-scale studies and generate evidence for its own health priorities. Her comments came before the fieldwork and the release of the preliminary results, but they provide context for the shift towards Ugandan leadership of the assessment.
At the October results announcement, Mikael Cleverley, the US Embassy Chargé d’Affaires similarly emphasised the significance of the country-led process. “The study was led by Ugandan scientists, Ugandan managers, Ugandan public servants, Ugandan field teams, from design to data collection to analysis,” he said.

He described the approach as the intended outcome of more than two decades of US health investment: strengthening national systems and enabling Uganda to lead its own response. The survey was funded by PEPFAR through the US CDC. Its findings will help the government and its partners determine where resources and services are most needed as Uganda approaches the 2030 deadline, said Cleverley.
Why the survey also measured other diseases
For the first time in the UPHIA series, the assessment included selected indicators of noncommunicable diseases (NCDs), expanding its focus beyond HIV. The preliminary findings showed that 15.5% of participants aged 15 and above had elevated blood pressure, 24.8% were overweight or obese, and 0.9% had elevated blood glucose.
These indicators provide an initial picture of selected chronic health risks in the surveyed population. They are not, by themselves, estimates of the total burden of diagnosed hypertension or diabetes, and the elevated blood glucose figure should not be interpreted as the prevalence of confirmed diabetes.
The inclusion of these measures reflects the Ministry of Health’s intention to strengthen integrated healthcare, bringing HIV services together with care for other chronic conditions. As people living with HIV live longer with effective treatment, health services increasingly need to address their broader health needs, including screening and care for conditions that may require long-term management. Integrating services can also help health facilities use patient visits to identify other health risks.
Dr. Baryomunsi said the evidence would support integration of HIV services with care for hypertension, diabetes and other priority conditions. The results provide a baseline for selected NCD indicators and may help inform decisions about screening, referral and chronic disease management. He said further analysis will be needed to understand how these conditions vary by age, sex and HIV status and what service changes would have the greatest impact.
The road to 2030
The preliminary UPHIA 2025 results show that Uganda’s HIV response has achieved strong treatment outcomes but has not closed the gap in diagnosis. The proportion of adults living with HIV who know their status remains below the 95% target, while prevalence has remained broadly stable since the previous survey. Young women face higher prevalence than young men, and viral suppression among younger people living with HIV is lower than among older adults. Regional differences also remain substantial.
These findings identify priorities for the next phase of the response; reaching people who have not been diagnosed, sustaining treatment outcomes, strengthening services for younger people and directing resources towards communities with the greatest needs.
But the preliminary survey does not yet provide all the evidence required to judge progress towards ending AIDS as a public health threat by 2030. The final results on HIV incidence and behavioural indicators will be important for determining whether new infections are falling and which prevention interventions require greater attention.
For now, the findings offer a clear measure of both progress and unfinished work. Uganda has brought treatment and viral suppression to high levels among people who have been diagnosed and are receiving care. The next challenge is to extend those gains to people who remain outside the reach of diagnosis and effective services, while using the new evidence to guide a more targeted, sustainable national response.
The post Uganda’s fight against HIV is far from over appeared first on The Independent Uganda:.