
Six months ago, Surekha Panicker (name changed), a 65-year-old retired professional from Kerala, stared at her diagnosis in shock—stage-2 breast cancer. She had no family and limited savings. She went to an oncologist at a leading private hospital to figure out a treatment plan. They decided on immunotherapy, particularly Roche’s injection Phesgo, which would cost Rs 5 lakh for the first loading dose of a 1,200 mg vial and over Rs 2 lakh for subsequent doses. She was offered a “buy one, get one” deal under Roche’s patient assistance programme— you pay for one cycle and the next will be free. She was prescribed eight cycles.
After two cycles, Panicker developed a severe bacterial infection and had to pause the treatment and go for surgery. The free offer lapsed due to the break. She has paid over Rs 35 lakh from her own pocket—for the treatment of the infection, the surgery, all subsequent cycles of immunotherapy and other hospital charges. Her funds are almost exhausted. Panicker doesn’t know how to pay for another course of treatment.
Also Read: NPPA caps trade margins on 137 cancer drugs at 30%, revised prices from Nov 9
“My husband died two decades ago. I have no kids or close relatives. I spent my savings on immunotherapy in the hope that it would buy me at least 10 years. I don’t know how I will manage if I need to continue the treatment,” says Panicker.
 ET Bureau
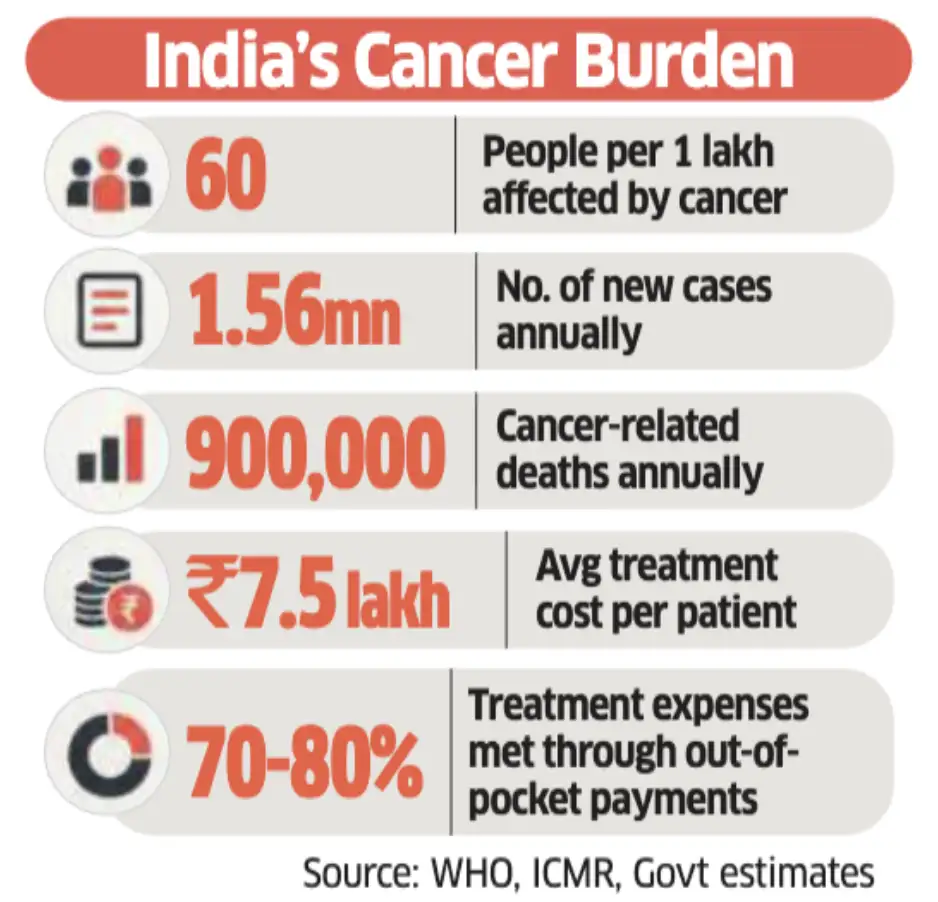
It is not just Panicker’s plight. Millions of cancer patients in India have to bear the double burden of the disease and the dreadfully expensive treatment.
A PRESCRIPTION AWAY FROM BANKRUPTCY
The high cost of cancer drugs is in full public glare after the Supreme Court criticised the massive markup in their prices. A bench of Justices Vikram Nath and Sandeep Mehta, hearing two writ petitions filed by lawyer Kishan Chand Jain and paediatric surge on Sanjay Kulshrestha, said medicines that are purchased by retailers for Rs 2,700 are being sold to patients for Rs 27,000. They called it “broad daylight dacoity”.
The anger of the bench resonates with the people. In a country where 1.5 million cancer cases are detected every year, a diagnosis very often leads to a long painful road of financial distress. Patients drain bank accounts, wipe out savings and even sell land just to get their hands on these promising but prohibitively expensive new medicines. How did India fail to make life-saving drugs affordable for its population?
A Mumbai-based oncologist says the situation is dire. “People are only a prescription away from bankruptcy,” he says.
Patients have no hope in the absence of a fair pricing mechanism, a pooled procurement plan by hospital networks and an effective insurance and reimbursement system, he says on condition of anonymity.
There are exceptions though. The Tata Memorial Centre in Mumbai procures drugs on a negotiated model, at rates that are far less than the maximum retail price (MRP), which makes them cheaper for its patients.
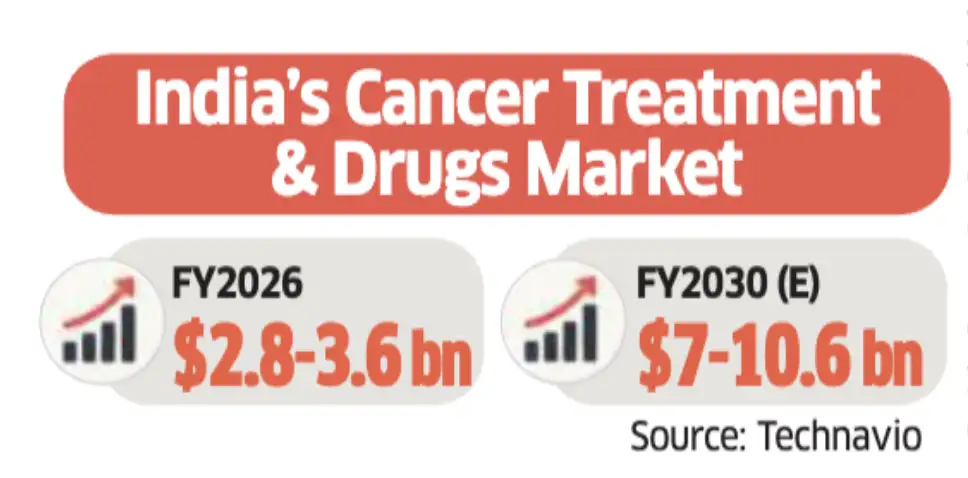
A study by top oncologists published in the Bulletin of the World Health Organization in 2023 showed that a pooled procurement of 40 drugs by the National Cancer Grid—a network of over 250 cancer centres—saved `13.2 billion compared with MRP. The savings ranged from 23% to 99%.
COST OF CARE
Top private hospitals do not agree that they are committing medical dacoity. In addition to the retail price of the medicine, they say, the hospital bill includes the cost of administration, use of facility, storage, training and consumables.
Abhay Soi, chairman and managing director of Max Healthcare Institute, says at the end of the day, a hospital is not selling an IV fluid bag. “A hospital is administering an injection. There is a particular training, a particular storage requirement, the administration of medicine and then the disposal through proper biomedical waste processes. There is an entire value chain,” he says.
Also Read: Supreme Court questions govt over drug pricing, asks why cap limited to anti-cancer medicines
Hospitals have thousands of individual billing items, with margins varying across products and services, he says. “Some won’t have a margin, some will have a margin. Ultimately, it translates to 8-9% net profit,” says Soi. He says hospital profitability needs to be viewed against the sector’s capital intensity and continuing investment requirements. “Your equipment gets totally depreciated. You replace the entire equipment every 10 years. Eventually, you must reinvest as well,” he says.
BS Ajai Kumar, founder of specialty cancer hospital group HCG Enterprises, backs Soi’s point. He says it is important to understand that India provides high-quality cancer treat ment at a much lower cost than many Western countries like US. Private hospitals, he adds, should be assessed not simply by the markup on an individual drug but the overall cost of treatment relative to the quality of care and outcomes delivered.
 ET Bureau
MARK THE MARKUPS
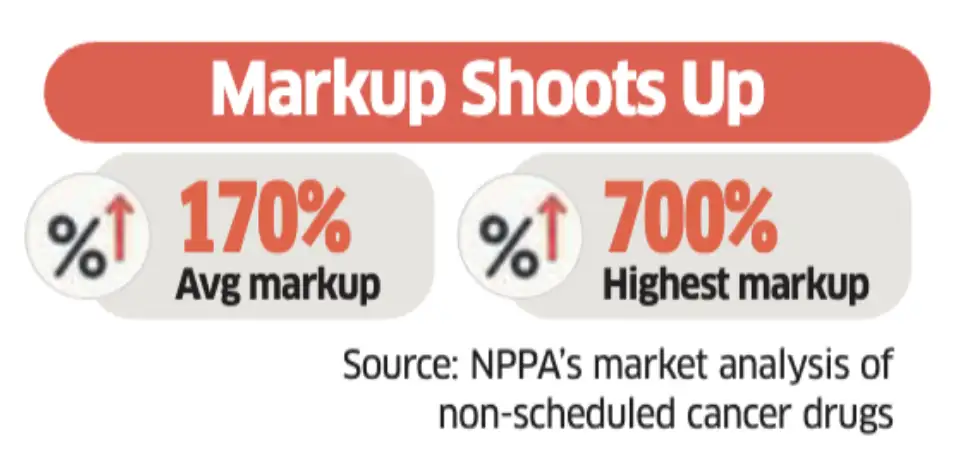
Health activists, however, note that hospitals lack transparency. They ask: what is the chain of markups from pharma manufacturers to distribution chains and healthcare providers?
In response to the Supreme Court’s criticism, the government has proposed a cap on trade margins for non-scheduled cancer drugs, which are not listed in Drugs (Prices Control) Order or DPCO.
The margin is proposed to be capped at 30% of MRP. This means drug purchased for Rs700 cannot be sold for more than Rs 1,000. The move, the government says, could bring down prices by up to 70% and can help patients save Rs 2,500 crore annually.
However, civil society and patient advocacy groups are not sure of the impact of this intervention. Several stakeholders, including doctors, told ET that the larger issue remains unresolved and several drugs, specifically patented drugs, are still exorbitantly priced. “Patient assistance programmes of MNCs, though well-intentioned, are not adequate,” says a health activist.
“High base prices, steep hospital markups and limited disclosure of procurement costs are behind the problem,” says Jain, who moved the petition in the apex court.
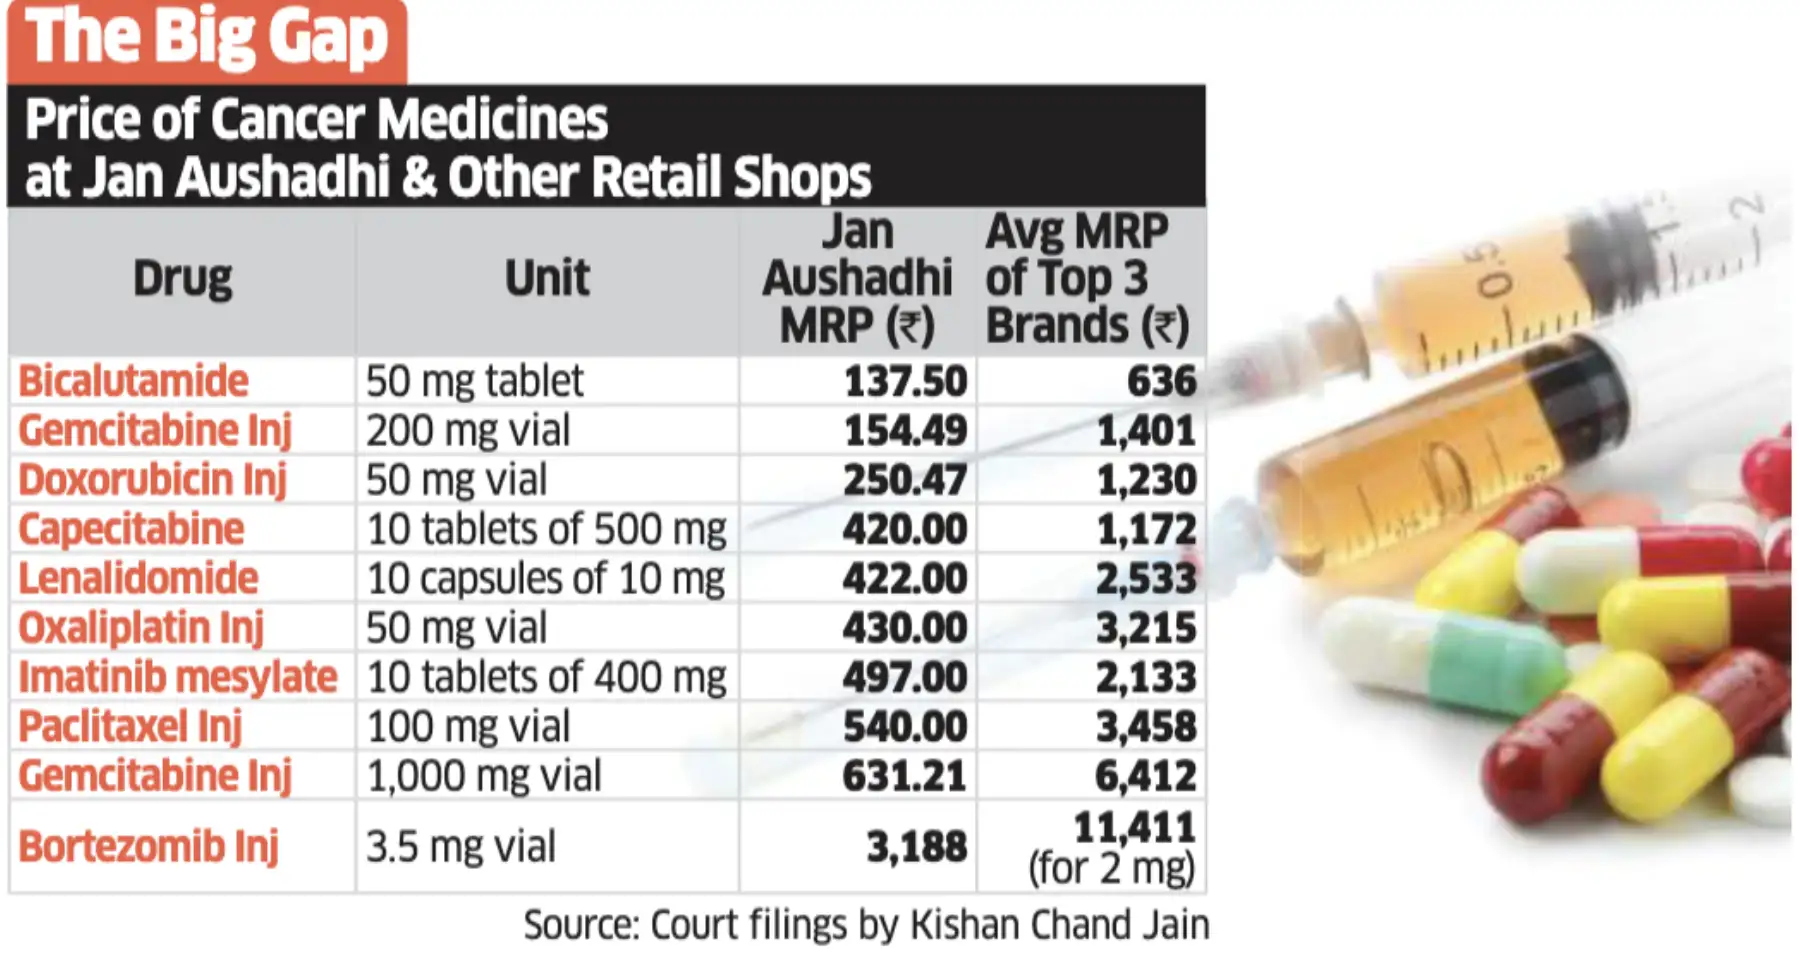
There is a huge difference in the prices of some cancer drugs sold through the Jan Aushadhi Scheme, the government’s fair price stores, and other retail shops, claims Jain’s petition. A 50 mg vial of doxorubicin injection costs Rs 250 at Jan Aushadhi, while the average price of top three brands for the same medicine in other retail shops is Rs 1,230 —an increase of over 390%. A 1,000 mg vial of gemcitabine costs Rs 631 at Jan Aushadhi and Rs 6,412 in other shops —a 916% increase.
Jain says trade margin for drugs should be calculated on the actual exfactory price or purchase price rather than as a percentage of printed MRP. A medicine purchased for Rs 700 can be given an MRP of Rs 1,000 under the new trade margin cap proposed by the government. But that markup of Rs 300 is still about 43% of the purchase price.
 ET Bureau
DIFFERENT PROBLEMS
Experts say the proposed margin cap of 30% will have an effect on drugs with exceptionally high markups. However,it will have little impact on patented cancer drugs that cost Rs 1.5-2 lakh for a vial and tens of thousands of rupees for a strip of tablets as their prices are not pushed up by markups.
Multinational companies supply their patented medicines based on a combination of factors—the country’s population and expected demand, international reference pricing, per capita income and paying or purchasing capacity of the country. “For patented medicines, margin capping does not work. And in the case of generic medicines, the regulation may not work on every drug,” says KM Gopakumar, co-con vener, Working Group on Access to Medicines and Treat-ments, a network of patients and activists fighting for affordable healthcare.
He says there should be a clear distinction between excessive hospital-level markups and high cost of patented drugs. The two problems may require different regulatory interventions.
Gopakumar cites a public interest litigation on the high cost of the breast cancer drug ribociclib. It cost Rs 78,000 for a month’s treatment before 2019 when the government regulated the prices of 42 cancer drugs. Ribociclib’s price has come down but it is still unaffordable at Rs 66,000.
TAXING MRP
Abhay Shukla, co-convener of Jan Swasthya Abhiyan, a national network on public health, also says markups will have limited impact. He says all cancer medicines should be brought under the scheduled price-control framework. “Drug prices must be determined by production costs rather than inflated market prices,” he says. “Regulators should first establish a medicine’s production cost and use that as the basis for determining a reasonable price, rather than rely on the prices charged by manufacturers.”
That may not be easy. Global drug firms price their new innovations based on comparable benefits over available treatment options and cost of research which runs into billions of dollars.
 ET Bureau
Shukla says pharmaceutical companies often print inflated MRPs and offer hospitals substantial discounts while hospitals sell the medicine to patients at the printed price. “Controlling the margins of hospitals alone does not address the problem if the MRP itself is inflated,” he says.
Besides, he says, DPCO covers only a fraction of the drug market, leaving a significant part—which includes many high-cost, life-saving drugs—outside the purview of direct price regulation or ceiling.
Scheduled medicines, which are under DPCO, account for only 17% or Rs 43,683 crore of the pharmaceutical market, while nonscheduled medicines account for Rs 2,15,294 crore or 83% of the market, estimated at Rs 2,58,977 crore, according to government data. The manufacturers of non-scheduled medicines can determine the launch price, but subsequent increases cannot exceed more than 10% annually.
The apex court has questioned the Centre on restricting price control to select cancer medicines, asking why similar measures are not being considered for other drugs.
Jain estimates that extending price reduction across the broader non-scheduled market could potentially save patients around Rs 1 lakh crore annually. “Profit should not mean profiteering,” he says.
The debate has spilled over, with even hospitals and medical insurance companies sparring over reimbursement rates. Top insurers are pushing for a regulatory mechanism for greater standardisation of hospital pricing and treatment protocols. Mayank Bathwal, CEO of Aditya Birla Health Insurance, says: “We don’t have a health regulator as it is a state subject. There must be a mechanism for regulation of healthcare services and pricing within certain norms so that whoever is investing is getting a fair return but, most importantly, consumers are provided affordable healthcare services.”
The Supreme Court has set in motion a much-needed debate on affordable cancer care. But patients like Panicker have a finite waiting time. They need a treatment within their means soon. The cost of remission should not be harrowing debt.