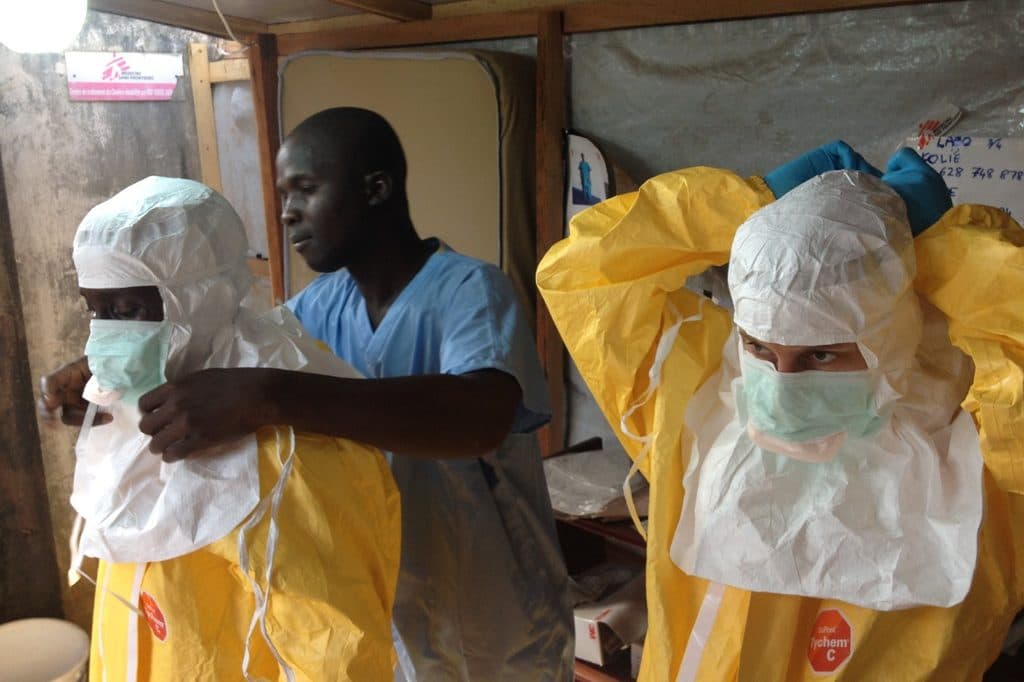
The Ebola outbreak in Africa and the emergence of imported cases in countries that were not at the center of the epidemic have once again put international health surveillance systems to the test. The Democratic Republic of the Congo is at the center of the main ongoing outbreak, caused by the Bundibugyo virus, while Kenya and Nigeria have confirmed infections linked to travel from affected areas.
The disease’s geographic spread raises a question for Colombia, particularly in light of its experience with the 2020 Covid-19 pandemic: Does the country have the resources and hospital capacity needed to contain an emergency of this kind?
The country has protocols in place to identify, isolate and treat suspected cases, as well as epidemiological surveillance mechanisms coordinated by the Ministry of Health and the National Institute of Health (INS). However, having established procedures does not necessarily mean being prepared to handle a large-scale emergency.
The response capacity would depend on early detection, protection for healthcare workers, the availability of appropriate facilities, and coordination between national and regional authorities.
Is Colombia prepared for an Ebola outbreak?
On Oct. 8, the World Health Organization (WHO) reported that the Bundibugyo virus disease outbreak had spread to another health zone in North Kivu, in the eastern Democratic Republic of the Congo. As of Oct. 6, the country had recorded 8,728 confirmed cases and 4,205 deaths, representing a crude case fatality rate of 48.2%.
The situation took on an international dimension with the confirmation of an imported case in Kenya and, subsequently, another in Nigeria. On Oct. 20, the WHO Regional Office for Africa reported that Nigeria had confirmed an infection in a woman with a recent travel history to Uganda. Authorities identified 44 contacts and activated isolation, surveillance and infection prevention measures.
These cases show that international travel can carry the virus into new territories, although they do not necessarily mean that a global pandemic will occur. The WHO continues to monitor the situation and has stressed the importance of rapid case detection, contact tracing and healthcare preparedness.
Nigeria has confirmed one imported case of #Ebola Bundibugyo virus disease in the Federal Capital Territory (FCT), becoming the fifth country to detect the virus since an outbreak of the disease was declared in the Democratic Republic of the Congo (DRC) on 15 May 2026.
As per the Federal Ministry of Health, Nigeria (@Fmohnigeria):
The patient is a woman with a recent travel history to Uganda.
The ministry, so far, reports that 44 contacts have been identified and are being monitored. Contact tracing is also underway.
Rapid identification of cases, timely follow-up of contacts and effective infection prevention and control are critical to contain the spread of the virus.
WHO and partners are working with health authorities to strengthen efforts to stop the virus from spreading.
WHO urges all countries in the region to sustain a high level of readiness as the outbreak in the DRC continues to evolve.
WHO advises against any restriction of travel to, or trade with, affected countries, and continues to closely monitor and, where necessary, verify travel and trade measures in relation to this event.
WHO regularly reviews the latest information to update its assessment of the risks posed by the outbreak.
Read the full press release: https://t.co/kM4nlqOGXe— World Health Organization (WHO) (@WHO) October 20, 2026
The Ministry of Health has specific guidelines for responding to a potential introduction of Ebola into the country. The measures cover the detection of suspected cases among travelers, initial care, isolation, safe patient transport, the handling of biological samples and waste, and contact tracing.
The INS has also conducted training and refresher courses aimed at strengthening surveillance and the response capacity of regional and local health authorities. These tools are an advantage because they make it possible to establish procedures as soon as a suspected case is identified and reduce the risk of transmission within healthcare facilities.
However, protocols are effective only if they can be implemented immediately. A suspected case requires trained personnel, appropriate protective equipment, isolation facilities, specialized transport, and coordination among hospitals, laboratories and health authorities. Any delay or failure in these measures can increase exposure among healthcare workers and other people.
Another challenge is recognizing the disease in its early stages. Fever, general malaise and other initial symptoms can be mistaken for diseases more common in Colombia, such as dengue or malaria. For this reason, knowing a patient’s travel history and potential contact with infected people is essential to guide diagnosis and activate the appropriate measures.
Healthcare inequalities, a decisive factor
Preparedness also depends on regional disparities. Major cities have specialized hospital services, but rural and remote areas may face greater difficulties transporting patients, obtaining diagnostic tests and ensuring timely isolation. In an emergency involving several simultaneous cases, these limitations could complicate the response and require additional resources.
International experience shows that containing the first infection depends on more than hospitals alone. It also requires contact tracing, adequate supplies of protective equipment, and clear public communication to prevent rumors and behaviors that could hinder healthcare efforts.
Coordination among the national government, health departments and medical institutions would be essential to prevent an imported case from triggering a chain of transmission.
Airports and other points of entry into the country are part of this strategy, as they were in 2020 during the Covid-19 pandemic. However, screening travelers is not enough on its own, since an infected person may cross a border before developing symptoms.
Epidemiological surveillance must therefore be complemented by the ability to identify cases later, investigate patients’ histories and act without delay.

The risk of a pandemic is not the same as the risk of local transmission
Ebola is not transmitted through the air like influenza or measles. It spreads mainly through direct contact with the blood and other bodily fluids of symptomatic infected people, as well as through contaminated materials. This makes timely isolation and infection prevention and control measures essential to interrupt transmission.
It is also important to distinguish the Bundibugyo virus, which is responsible for the current outbreak, from other Ebola species. According to the WHO, there is currently no licensed vaccine or specific treatment for this variant, although potential alternatives are being investigated.
This situation reinforces the importance of prevention, supportive clinical care and a rapid response by authorities. The circumstances do not justify raising alarm in Colombia, nor do they support claims that the country faces an imminent threat of community transmission.
They do, however, make it necessary to maintain surveillance, update contingency plans and ensure that the planned resources are available when needed.
In this regard, Colombia has tools to respond to the potential arrival of an Ebola case, but this is not enough to establish that the country is fully prepared to handle a pandemic on a large scale. To demonstrate such preparedness, the country would need to turn its protocols into verifiable operational capacity, with trained personnel, sufficient supplies, reliable diagnostic capabilities and effective coordination throughout the country.
The African outbreak shows that early detection and contact tracing can contain imported infections, but it also demonstrates that any delay makes the challenge more difficult.