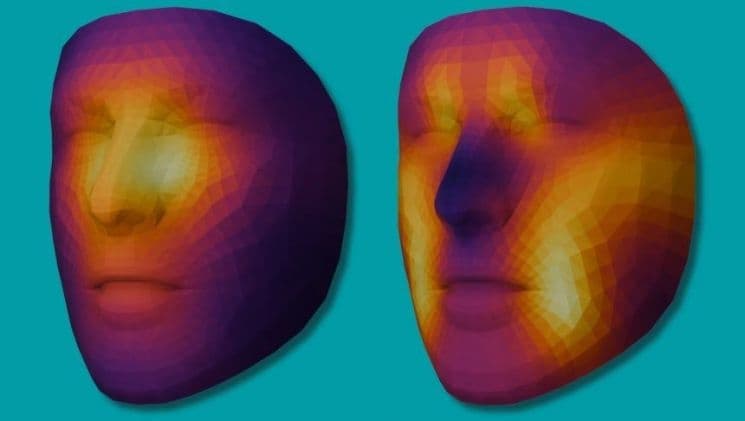
Researchers have developed artificial intelligence tools that estimate a cancer patient's risk of death from a single photograph of the face. The team expects the tools to be especially useful in settings where medical data are scarce.
Researchers at the Mass General Brigham Cancer Institute published their findings on the 20th in the medical journal The Lancet Digital Health. Bloomberg reported the news, citing the paper. The team trained a foundation model on more than 40 million facial images, then further trained it on 34,000 photographs of cancer patients to build two tools. One, called FAHR-FaceAge, estimates biological age from a face. The other, FAHR-FaceSurvival, produces a mortality risk score for individual patients.
Patient groups with higher scores showed substantially higher actual mortality risk. A gap in mortality risk between the two groups was also confirmed. The tools worked the same way across patient groups that varied by age, race, sex and cancer type.
Raymond Mak, a radiation oncologist at the Mass General Brigham Cancer Institute, said, "Doctors are trained to assess a patient's health by looking at their appearance in the exam room." He said a facial photograph alone can reveal part of a patient's physiological reserve and mortality risk. Mak said he was surprised by the model's predictive performance. Feeding both the face-age score and the survival score into clinical prognostic models improves survival prediction compared with using either one alone, he said.
The same team reported face-photo-based research in May 2025. At the time, it trained a biological age model on about 59,000 facial photographs and applied it to about 6,200 cancer patients. Cancer patients were estimated, on average, to be about five years older than their actual age.
An outside expert who did not take part in the study praised the findings but cautioned against rushing into clinical use. Predicting an outcome is different from explaining why it occurs, the expert said, adding that it has yet to be proven that the tools provide clinically useful information beyond a physician's overall assessment. Others argued the models must be validated at other hospitals and in different patient populations. A science publication noted as a limitation that the models were trained largely on white patients in the Boston area.